

WHY THIS RESOURCE EXISTS
Human milk is the physiologic norm for infant nutrition. It is becoming more and more apparent that breastfeeding has long-lasting health benefits for the mom. However, the use of medications in breastfeeding mothers is often controversial and is steeped with misinformation in the healthcare field. Prescribers commonly extrapolate pregnancy data to lactation, confuse “no evidence of harm” (due to lack of studies) with “evidence of no harm” (from adequate research), or default to package insert recommendations written for legal protection rather than clinical guidance. This product has for many years been the primary source for drug information in breastfeeding mothers. The truth is, most drugs simply don’t enter milk in levels that are hazardous to a breastfed infant. The problem, however, is determining which drugs are safe and which are hazardous.
Because so few clinicians understand lactational pharmacology (a subject rarely taught in medical, pharmacy, or nursing programs), the number of women who are advised to discontinue breastfeeding in order to take a medication is still far too high. Ironically, the mothers with the most to gain from breastfeeding (those with chronic conditions, lower incomes, or limited access to healthcare) are often the ones being told to stop in order to take medications. Fortunately, many mothers are now becoming aware of the importance of human milk and advocate for themselves and their babies. Unfortunately, now that mothers value breastfeeding, they frequently avoid necessary medications in an attempt to prevent harm to their infant, at the risk of their own health.
Because almost all mothers will ingest medications postpartum, it is not surprising that one of the most common questions encountered in pediatrics concerns the use of various drugs in the breastfeeding mother. Unfortunately, most healthcare professionals simply review the package insert, generic drug references, or advise the mother not to breastfeed without having done a thorough study of the literature to find the true answer. Discontinuing breastfeeding is often the wrong decision, and most mothers could easily continue to breastfeed and take the medication without risk to the infant. The FDA now recommends drug manufacturers study milk levels of their medications, though labeling still lags behind the evidence.
When evaluating medication use during breastfeeding, consider what happens without treatment. Untreated maternal illness carries its own risks—to the mother’s ability to care for her infant, and sometimes to the milk itself. The question is rarely “medication versus no medication.” It is medication versus the consequences of untreated disease.
It is generally accepted that all medications transfer into human milk to some degree, although it is almost always quite low. Only rarely does the amount transferred into milk produce clinically relevant doses in the infant. Ultimately, it is the clinician’s responsibility to review the research and make shared decisions with mothers as to the best choices in these cases. This product exists to give you the evidence you need to make these decisions with confidence. But evidence alone isn’t always enough—understanding the human side of these decisions matters too.
THE HUMAN ELEMENT
Everyone has a different threshold for risk—providers and mothers alike. Many mothers believe that being a good mom means protecting their infant, even at the cost of their own health. When faced with uncertainty, some don’t tell their prescriber they’re breastfeeding because they’re afraid of being told to stop or judged for continuing to breastfeed. Others are told to stop and choose not to take the medication at all. Neither situation serves the mother or the infant well.
No one wants to be told they aren’t being a good mom. They want to do the right thing - and they want your help to do it. The uncertainty has to be addressed and managed. Acknowledging the worry and identifying shared ground between mothers and healthcare providers is where you can identify incorrect assumptions, educate in ways that matter, and help ensure that whatever choice is made, it will be informed. Be a safe place for them.
Mothers and providers often have different thresholds for risk. A provider focused on avoiding any theoretical infant exposure may recommend stopping breastfeeding or avoiding treatment. A mother focused on continuing breastfeeding may not disclose her medication use - or may skip doses, alter her regimen, or abandon treatment entirely. Neither approach serves the goal: maximizing the health of both mother and infant.
Breastfeeding is not just infant nutrition. It is a health intervention for mom and baby. Maternal health supports infant health; breastfeeding supports maternal health. These are not competing interests to be weighed against each other - they are linked. When medication decisions force an unnecessary choice between them, both suffer.
This product exists to support informed clinical decisions. The evidence here does not make decisions for you. It gives you and the mother the information needed to find the path that optimizes outcomes for all.
PREGNANCY AND LACTATION ARE NOT THE SAME
Prescribers commonly extrapolate pregnancy safety data to breastfeeding. This is a mistake.
It seems obvious that pregnancy and lactation are different, but “pregnancy and lactation” are so often lumped together in guidelines, package inserts, and clinical thinking that the distinction gets lost. Lactational pharmacology is rarely taught. Without that foundation, it is easy to forget what we already know. When data are lacking, go back to fundamentals.
During pregnancy, drug travels one step: from maternal blood across the placenta (a selective barrier) into fetal blood. The fetus receives drug at concentrations often approaching maternal levels, continuously, for months. The maternal liver and kidneys clear drug for the fetus.
During lactation, the path is longer. Drug must cross from maternal blood into milk (again, a selective barrier). The infant must drink the milk. The drug must survive stomach acid and digestive enzymes. It must cross the intestinal lining (yet another selective barrier). It must pass through the liver, where first-pass metabolism may clear the drug entirely, before ever reaching infant circulation.
Most drugs don’t make it.
Drug exposure via breastfeeding is almost always far lower than exposure in utero. Safety data from one period cannot be applied to the other. A drug safe in pregnancy - when maternal organs did the clearing - may pose concerns when the infant must handle it alone. A drug avoided in pregnancy due to effects on fetal development may be fine during breastfeeding, when organogenesis is complete and exposure is a fraction of what it was.
Further, some drugs alter milk production. This has no parallel in pregnancy.
Evaluate pregnancy and lactation separately.
THE CORE ELEMENT
Drug transfer across the mammary epithelium has long been the focus of lactational pharmacology - and for good reason. But transfer is only half the equation. A drug can only cross into milk if it is present in maternal plasma first. Maternal plasma concentration sets the ceiling; transfer characteristics determine how much of that ceiling is reached.
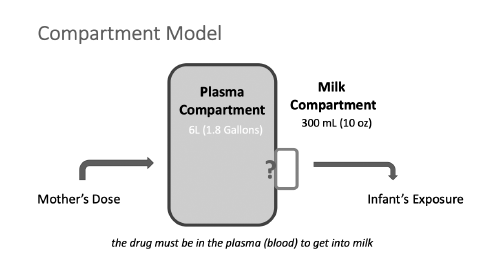
This reframes how we think about familiar kinetic parameters. When we say high protein binding and high volume of distribution are “protective,” they are actually limiting free drug concentrations in maternal plasma. Transfer from low plasma concentrations will virtually always result in low milk concentrations. The barrier matters, but what’s available to cross it matters just as much.
A practical way to think about this: if the mother can feel the drug’s effects, it is in her plasma (and CNS) and therefore available to transfer into milk. This is why we advise caution during peak effects of alcohol, opioids, or sedatives. When the mother feels impaired, the drug is in her system. When the effects wear off, plasma levels are falling and milk levels follow.
The amount of drug in maternal plasma depends first on how much reaches systemic circulation. A topical cream, an inhaled medication, and an oral tablet of the same drug will produce vastly different plasma levels. Route and bioavailability set the ceiling for everything that follows.
Active metabolites also matter. Some drugs are metabolized into compounds that retain pharmacologic activity. These metabolites circulate in maternal plasma alongside the parent drug and can transfer into milk independently. A drug with a short half-life may produce metabolites with much longer half-lives, extending the window of exposure. When evaluating a drug, consider not just the parent compound but any active metabolites - their potency, their half-lives, and their presence in maternal plasma.
| When evaluating any drug, consider: |
|---|
|
By understanding what limits drug in maternal plasma, clinicians can estimate (and often minimize) milk concentration. But plasma is only the beginning. The complete pathway includes transfer across the blood-milk barrier, the infant’s own absorption and metabolism, and the clinical context in which decisions are made.
Clinical Decision Framework for Medications and Breastfeeding
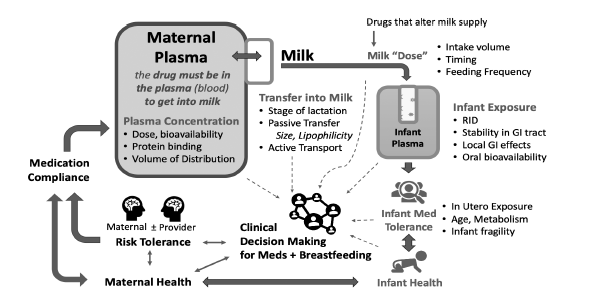
The sections that follow explain each step in this pathway.
| Drugs are less likely to reach the infant when: |
|---|
|
Maternal plasma levels are low:
Transfer into milk is limited:
Infant systemic absorption is unlikely:
|
WHAT LIMITS FREE DRUG IN MATERNAL PLASMA
Dose, Route, and Bioavailability
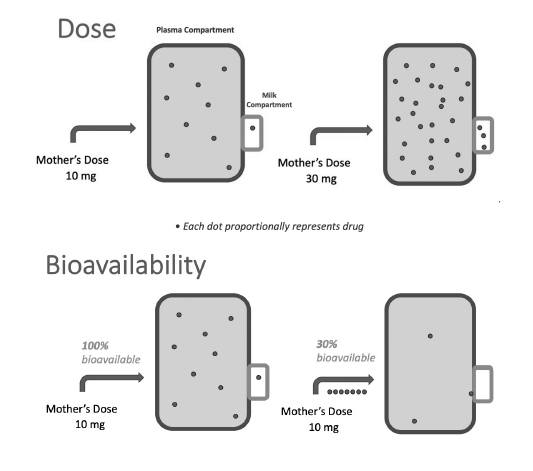
The amount of drug reaching maternal plasma starts with dose, but route and bioavailability determine how much of that dose actually gets there. Higher doses produce higher plasma levels, and therefore higher milk levels. It is always recommended to use drug doses evaluated in lactation studies. We often see doses up to five times higher than those researched, limiting the generalizability of the findings. Oral bioavailability determines how much of an oral dose actually reaches circulation. Poorly absorbed drugs (many topicals, inhaled meds) may never achieve meaningful plasma levels. When possible, use the lowest effective dose and consider routes that minimize systemic absorption.
Protein Binding
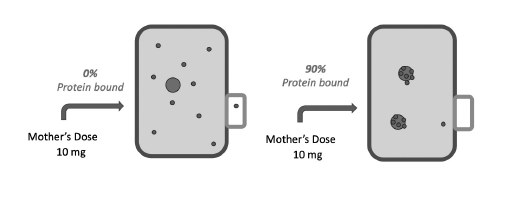
Protein binding is the most reliable predictor of drug concentration in milk. Drugs circulate in the maternal plasma either bound to a protein like albumin or freely soluble. It is the free component that transfers into milk, while the bound fraction stays in the maternal circulation. Drugs with high protein binding (>80%) have low milk levels simply because they are bound in the plasma compartment and can’t get out. Even moderate binding (60%-80%) significantly limits milk concentrations. Choose drugs with high protein binding.
Volume of Distribution
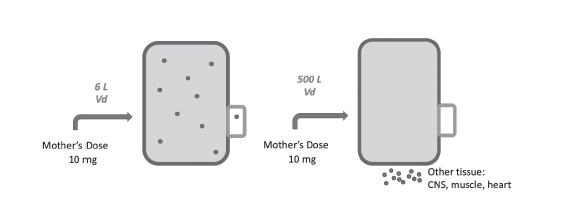
The volume of distribution describes how widely a medication distributes in the body. A small Vd (near plasma volume, ~0.04 L/kg) means the drug stays in blood, available to transfer. A large Vd (>1-2 L/kg) means the drug disperses outside the blood (muscle, organs, CNS, etc.), keeping plasma concentrations low. CNS-active drugs must distribute outside plasma to work, which paradoxically makes many safe during breastfeeding despite their potency, like ketamine. Choose drugs with higher volumes of distribution.
WHAT LIMITS TRANSFER INTO MILK
The Colostrum Period
During the first 72 hours postpartum, large gaps between alveolar cells permit enhanced access into milk for most drugs, immunoglobulins, and maternal proteins. By the end of the first week, alveolar cells close these gaps, reducing transfer. While drugs penetrate at higher levels during the colostrum period, the absolute dose transferred is still low due to the minimal volume produced (30-100 mL/day).
Passive Diffusion
Drugs normally enter milk by passive diffusion, driven by equilibrium forces between the maternal plasma compartment and the milk compartment. They pass from maternal plasma through capillaries into the lactocytes lining the alveolus. Medications must generally pass through both bilayer lipid membranes of the alveolar cell to penetrate milk.
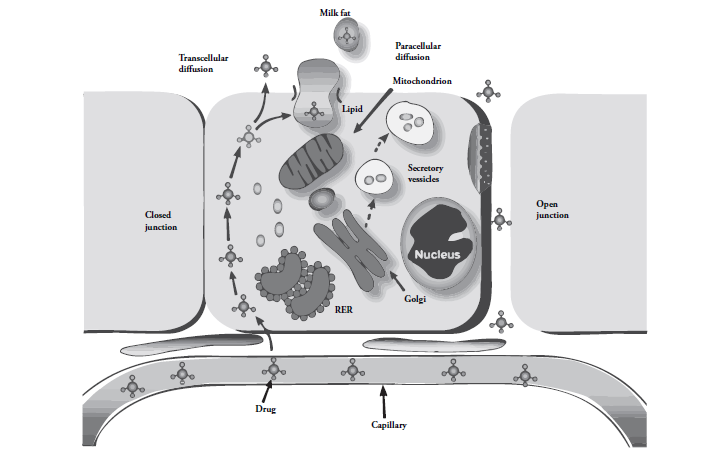
Drug properties determine how readily a drug crosses passively:
Molecular Weight. One of the primary reasons drugs cannot readily penetrate into milk is simply the size of the molecule. Water-filled pores in the lactocytes permit free movement of molecules with a molecular weight less than 200 Daltons. Passive diffusion becomes more difficult as size increases, until molecules are simply too large (around 500 Daltons) to be readily found in milk unless active transport is involved. Protein medications such as heparin and insulin have enormous molecular weights and are virtually excluded from human milk. When possible, choose drugs with higher molecular weights to reduce entry into milk.
Lipid Solubility and Ionization (pKa). Molecules must dissolve through the lipophilic phospholipid bilayer of cell membranes to reach milk. Drugs that are lipid-soluble or nonionized pass through more readily. The same principle holds true for the blood-brain barrier - drugs that enter the CNS have the characteristics needed to enter milk. If a drug is active in the central nervous system, significant levels in milk can be expected, although amounts are often still subclinical. Many neuroactive drugs produce relative infant doses above 5%.
Most of the time, ionization is not the deciding factor. But when it matters, it can matter a lot. The pKa of a drug determines the proportion that is ionized at a given pH. Milk is slightly more acidic than plasma (pH 7.0 vs. 7.4). Most of the time, this difference is not clinically significant. But for weak bases with high pKa, it can matter a lot. These drugs become ionized in the more acidic milk and trapped - they cannot easily cross back into maternal plasma. This “ion trapping” draws more drug across to maintain equilibrium, resulting in higher milk concentrations than expected. Cocaine is a classic example: its pKa of 8.6 leads to M/P ratios of 1.1-6.4.
Active Transport
Some cellular pumping systems actively transport drugs into milk against the concentration gradient from a low plasma concentration to a higher milk concentration. The risk of potential active transport of a drug into milk at unexpectedly high concentrations is the threat to infant health many fear, as can happen with iodine.
WHAT LIMITS INFANT EXPOSURE
Milk Intake and Timing
The amount of drug an infant receives depends not only on the concentration in milk, but on how much milk they consume. Milk intake varies considerably with infant age. In the first few days postpartum, colostrum volume is low, limiting absolute drug exposure even when milk concentrations are higher. By 1 month, most infants consume approximately 150 mL/kg/day, the standard assumption used in RID calculations. Older infants receiving solid foods take less milk, reducing their exposure.
Timing of breastfeeding relative to maternal dosing can further reduce infant drug exposure. Drug levels in milk parallel maternal plasma levels; they rise and fall together. For drugs with short half-lives, feeding just before a dose (when plasma levels are lowest) or waiting until after the peak has passed can meaningfully reduce the infant’s dose. For drugs with long half-lives or extended-release formulations, timing matters less because plasma levels remain relatively constant.
“Pump and dump” is often misunderstood. It does not speed drug clearance from milk - the drug clears as maternal plasma clears. Pumping and discarding is only useful when milk must be removed for comfort while waiting for a drug to clear, or to maintain supply during a temporary interruption. For most medications, it is unnecessary.
Local Effects in the Infant Gut
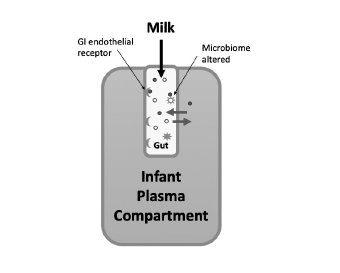
Before infant systemic absorption, drugs may exert effects within the infant’s gastrointestinal tract. This is largely theoretical - few drugs have documented local GI effects in breastfed infants - but it warrants consideration. Antibiotics in milk can alter infant gut flora. Drugs that cause GI side effects in adults (diarrhea, constipation, cramping) could potentially do the same in the infant gut before being eliminated.
In practice, clinically significant local GI effects are uncommon at the low concentrations present in milk. When they do occur, diarrhea is the most frequently reported. The more major concern is usually systemic absorption, not local effect. However, if an infant develops unexplained GI symptoms during maternal drug therapy, local effects should be considered.
Infant Oral Bioavailability and GI Stability
Once a drug has entered the mother’s milk and has been ingested by the infant, it must traverse through the infant’s GI tract prior to absorption. Some drugs are poorly stable in this environment due to the proteolytic enzymes and acids present in the infant’s stomach. This includes the aminoglycoside family, omeprazole, and large peptide drugs such as heparin and most monoclonal antibodies. Other drugs are poorly absorbed by the infant’s gastrointestinal tract and do not enter the infant’s bloodstream.
Many drugs, such as the aminoglycosides, vancomycin, and cephalosporin antibiotics (third-generation), are so poorly absorbed that it is unlikely the infant will absorb significant quantities. Proteins (including monoclonal antibodies) are naturally digested in the infant gut. This is why most biologics are compatible with breastfeeding despite their detection in milk - they are destroyed before absorption.
Absorption characteristics such as these ultimately tend to reduce the overall effect of many drugs in breastfed infants.
First-Pass Metabolism
When molecules are absorbed from the gut into the infant blood supply, they are directly sent to the liver for processing/ metabolism. Many orally administered drugs are sequestered in the liver (first pass) and may never actually reach the plasma compartment. First-pass metabolism will greatly reduce oral bioavailability of many drugs in milk, preventing systemic effects. Some transdermal patches, buccal, or intranasal formulations intentionally circumvent this effect for higher systemic levels.
Infant Age and Maturity
It is very important to always evaluate the infant’s ability to handle small amounts of medications. Some infants, such as premature or unstable infants, may not be suitable candidates for certain medications.
Infant drug clearance changes rapidly in the first weeks of life. By 8 weeks, infants have reached approximately 50% of their adult renal metabolic capacity, rising to 90% by 1 year. Drugs cleared primarily by the kidneys become less of a concern relatively quickly.
Hepatic metabolism is a different story. Infants do not simply have immature versions of adult enzymes - they have different CYP enzyme profiles entirely. Some pathways are deficient, others are more active than in adults, and the balance shifts over the first months and years of life. Drugs heavily dependent on hepatic metabolism may be cleared very differently in infants than in adults, and the direction of that difference is not always predictable.
| Evaluation of the Infant |
|---|
|
In Utero Exposure
During pregnancy, the maternal liver and kidney serve as detoxification and excretion resources for the fetus via the placenta, whereas during lactation an infant must handle the drug totally on their own after it has reached their circulation. An infant in utero receives drug in greater quantity via the circulation, whereas a nursing infant receives only what reaches the milk. Infants born with in utero exposures can be “loaded” with plasma drug levels that are compounded by lactation exposures.
DOES THE AMOUNT MATTER? (Potency and Therapeutic Index)
Plasma Concentration Drives Effects
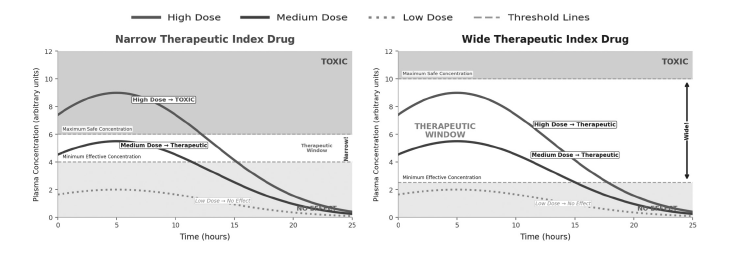
For both mother and infant, plasma concentration determines systemic effects. An infant receiving drug via milk is usually receiving a very small dose. This does not mean they are getting proportionately small effects, it means they are usually staying below the minimum effective concentration (MEC) where no effect occurs. For many drugs, the small amounts transferred via milk never approach these thresholds.
Therapeutic Index
Not all drugs behave the same way at low doses. Some drugs have a wide margin between “no effect” and “toxic effect.” These drugs have a large therapeutic index and are generally forgiving. Others have a narrow window: a small increase in plasma concentration moves quickly from no effect to therapeutic effect to toxicity.
A low RID of a drug with a narrow therapeutic index may still be concerning. A higher RID of a wide-index, lowtoxicity drug may be clinically irrelevant. Fluconazole has a high RID but is relatively non toxic and rarely bother infants. Ergotamine and cytotoxic agents require much lower thresholds for concern regardless of their RID.
Comparing Therapeutic Windows With Drug Concentration-Time Curves
Monitoring for Infant Adverse Effects
Without formal research, monitoring for adverse effects in breastfed infants is often the best we can do. Each monograph in this product includes infant monitoring parameters based on the known side effect profile of the drug and any reports from breastfeeding exposure.
In practice, few drugs have documented adverse effects in breastfed infants. The most commonly re ported drugs are also the most commonly used: pain medications (particularly opioids), sedating medications such as anxiolytics (benzodiazepines), and combinations of the two. Sedation, poor feeding, and respiratory depression are the effects most frequently observed. These reports have shaped our understanding of which drugs warrant closer monitoring.
For most medications, routine observation is sufficient. Watch for symptoms that parallel the drug’s known side effects in adults. When specific concerns exist, they are noted in the infant monitoring section of each monograph.
MEASURING EXPOSURE
Quantifying how much drug reaches the infant via milk has been a challenge since the beginning of lactation pharmacology. The milk/plasma ratio (M/P) was once commonly used to estimate drug transfer. We no longer rely on it because it is difficult to interpret for clinical use. A high M/P ratio sounds concerning, but if the maternal plasma level is very low, the absolute amount of drug in milk will still be low. Conversely, a low M/P ratio provides false reassurance if maternal plasma levels are high. Timing is also crucial. The M/P ratio changes throughout a dosing interval as plasma and milk concentrations rise and fall at different rates. A single M/P measurement tells you very little. The M/P ratio is reported in the monographs for reference, but it does not provide the clinician with reliable information about the actual dose transferred to the infant via milk.
What RID Is
One of the more popular methods for estimating risk to the infant is the relative infant dose (RID). The RID is not the percent of mom’s dose that gets to the baby. The RID is the percent of an infant-sized dose a fully breastfed infant will receive via breast milk, usually calculated by dividing the infant’s dose via milk (mg/kg/day) by the mother’s dose in mg/kg/day multiplied by 100. When standard infant doses are available, the infant dose (mg/kg/day) is preferred over the maternal dose in the denominator. The RID gives the clinician a feeling for just how much medication the infant is exposed to on a weight-normalized basis.
Many researchers suggest that anything less than 10% of the maternal dose is probably safe. This is usually correct. However, some drugs (metronidazole, fluconazole) actually have much higher RIDs, but because they are quite non toxic, they do not often bother an infant. With risky drugs such as anticancer agents, a much lower RID should be used in your evaluation of risk.
How RID Is Calculated
Please understand that many authors use different methods for calculating RID. Some are not weight-normalized. In these cases, their estimates may differ from this resource. While I often include the authors’ estimates of RID, the RID range in this product is calculated based on a 70-kg mother and is weight-normalized in all instances. I also chose the data I felt was best, which often included larger studies with AUC calculations of mean concentrations in milk. The RID assumes a daily milk intake of 150 mL/kg/day in the infant. Please note many authors fail to normalize their data for weight. Others provide a RID for each feeding, not a daily average. Therefore, values may vary slightly from others simply due to differences in calculation method.

RID Limitations
Dose matters. Though the RID percentage remains the same, higher maternal doses result in higher absolute infant exposure.
Bioavailability mismatch. The RID equation does not consider bioavailability, which may be mismatched between the maternal route and infant oral consumption. A maternal IV or topical dose may result in very different plasma levels than the same oral dose, but RID calculations often do not account for this. Dismissing bioavailability typically overestimates infant drug exposure via milk.
Long-acting formulations. The RID equation does not accommodate infrequent dosing of drugs formulated to remain systemically available over extended periods. Lactation studies on these drugs commonly include the entire maternal dose in the denominator compared to a 24-hour infant dose via milk. This results in an artificially low RID that does not accurately reflect the risk.
The bottom line: Although there are limitations to the use of RID to predict drug safety, an appropriately calculated and reported RID can be useful when it is low and is thoughtfully combined with other important drug information. After four decades, we have more tools to build metrics for lactation pharmacology, but they are still lacking, mostly due to the paucity of data. Other metrics are evolving but not widely available. Until we know more, RID combined with maternal dose and kinetic understanding are our best tools to evaluate drugs.
THE GOAL: MATERNAL AND INFANT HEALTH
The purpose of this product is not to unilaterally determine whether a drug is “safe” or “unsafe.” It is to provide the evidence needed for informed clinical decisions that maximize the health of both mother and infant. These are not separate goals. Breastfeeding benefits both. Maternal wellbeing supports infant wellbeing. When we help mothers access treatment without unnecessarily interrupting breastfeeding, we serve both.
| Key Points About Breastfeeding and Medications |
|---|
|